

Selecting the Best Neuronavigation-Capable Surgeons and Hospitals in India — A Congolese Patient's Guide
A practical guide for Congolese patients comparing neuronavigation-capable brain surgery teams in India, with emphasis on lesion-specific expertise, technology verification, neuro-ICU support and costs.
Advanced technology is easy to mention in a brochure and much harder to verify from a distance. In 24 years of helping families through this exact choice, I have learned that the gap between a centre that genuinely uses neuronavigation in daily practice and one that simply lists it on a website is often invisible until it is too late to matter. This guide sets out, plainly, how to close that gap before you travel. The questions below are deliberately specific, because vague reassurance is exactly what a family cannot verify from Kinshasa.
Healing Journeys of Congolese Patients







Key Takeaways
- The guide explains that neuronavigation is not necessary for every brain lesion. It is most relevant when a lesion lies near or within an eloquent brain area affecting speech, movement, vision or memory. Patients should first confirm whether the technology genuinely changes the risk profile of their specific operation.
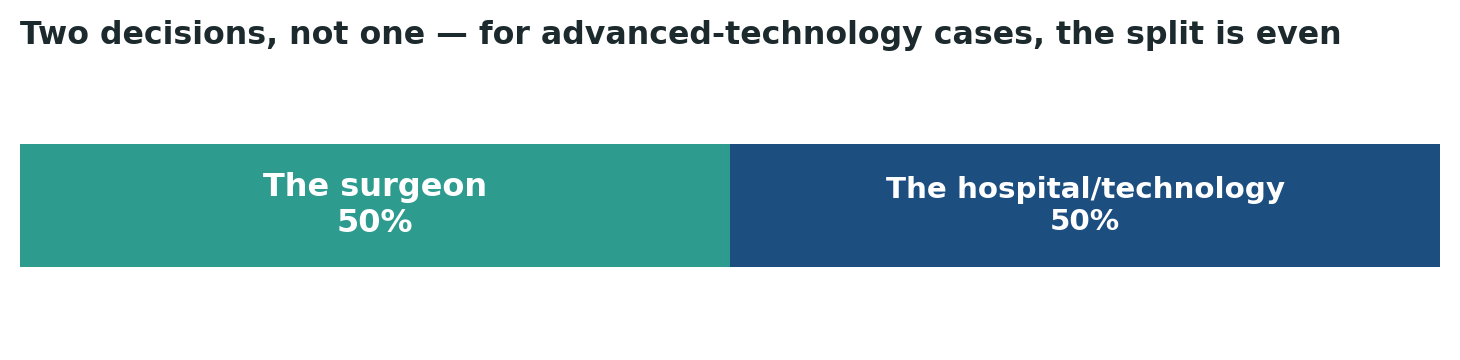
- The page 2 graphic gives equal 50% weighting to the surgeon and hospital/technology, emphasising that advanced equipment is only useful when a suitably trained specialist can use it effectively. The guide recommends a named sub-specialist in eloquent-area surgery and case volume for the exact lesion location during the previous 12 months.
- The surgeon's qualifications should be verified beyond a website title. The guide's qualification ladder progresses from MBBS and MS General Surgery to MCh/DNB Neurosurgery and fellowship training in skull-base or functional neurosurgery, with the fellowship specifically relevant to image-guided and eloquent-area surgery.
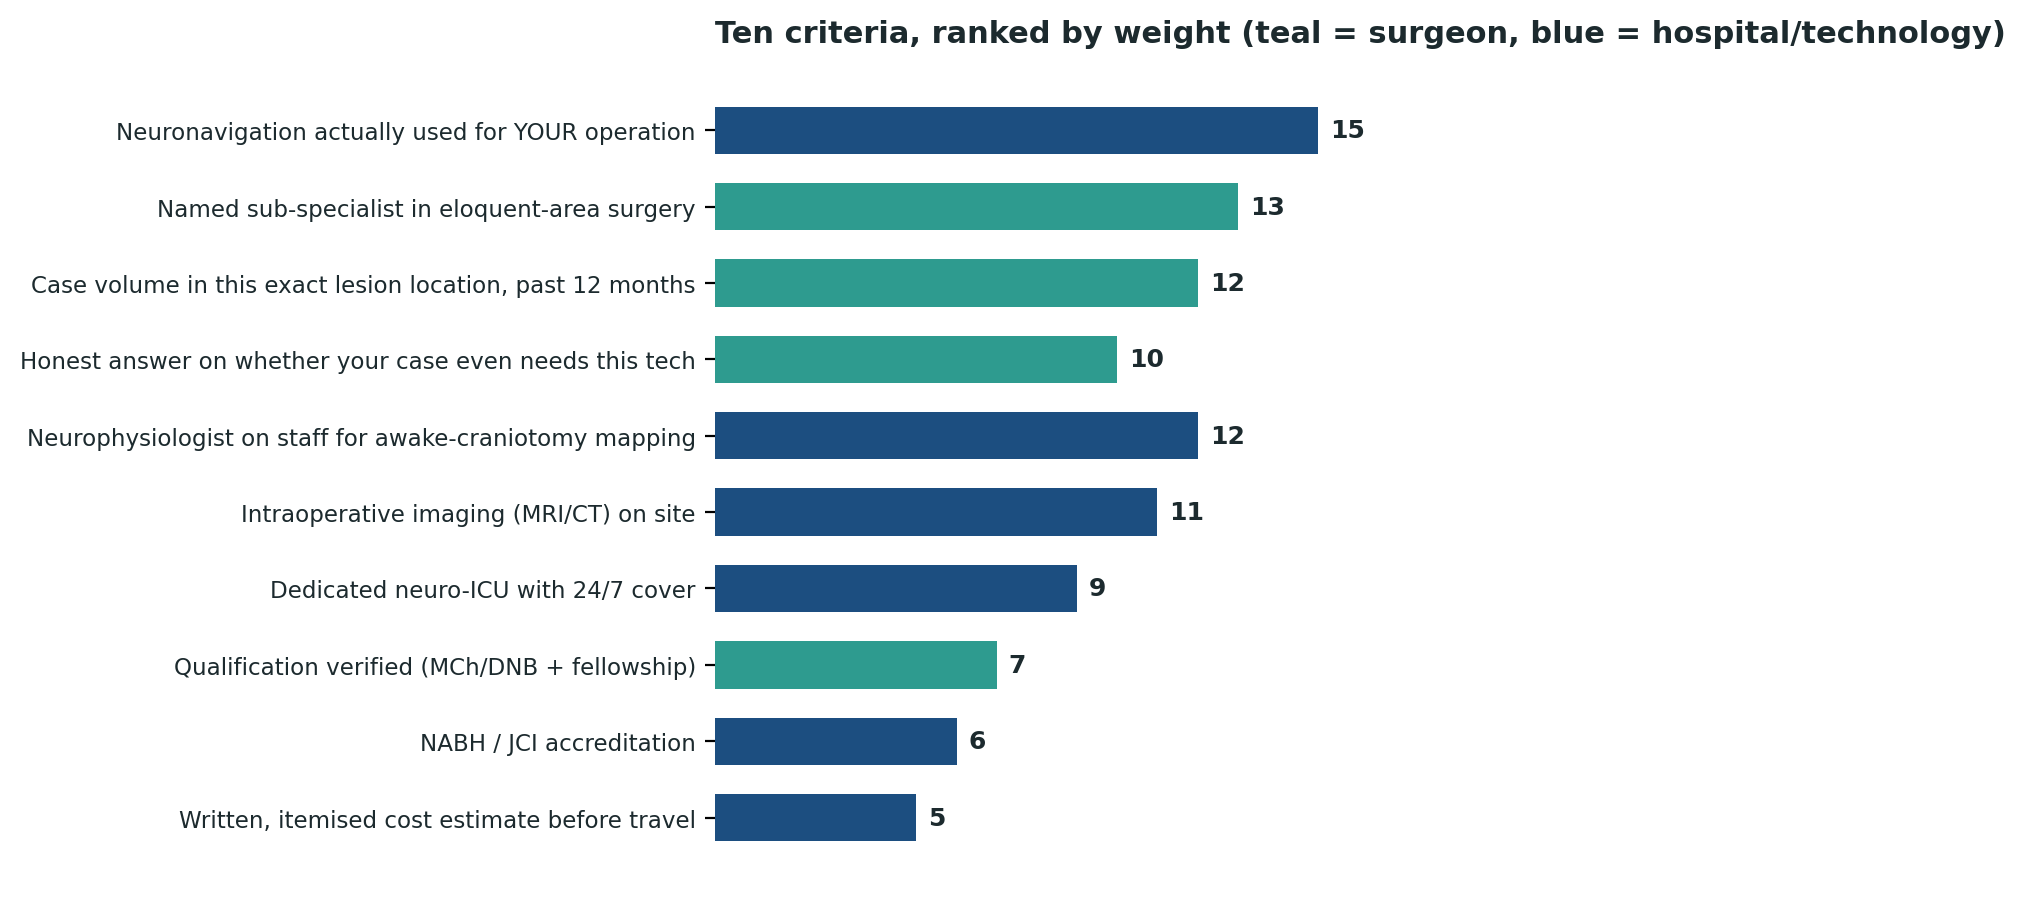
- The page 3 criteria chart ranks neuronavigation actually being used for the patient's operation highest at 15 points, followed by a named eloquent-area sub-specialist at 13, exact-lesion case volume and a neurophysiologist for awake-craniotomy mapping at 12 each, and intraoperative MRI/CT availability at 11. Dedicated neuro-ICU care, verified qualifications, accreditation and written costs receive additional weighting.
- The guide stresses that hospitals should confirm neuronavigation is routinely used, intraoperative MRI or CT is genuinely on site when required, a trained neurophysiologist is available for mapping and a dedicated 24-hour neuro-ICU is provided. Patients should obtain written confirmation that the equipment will be used specifically during their scheduled operation, not merely that the hospital owns it.
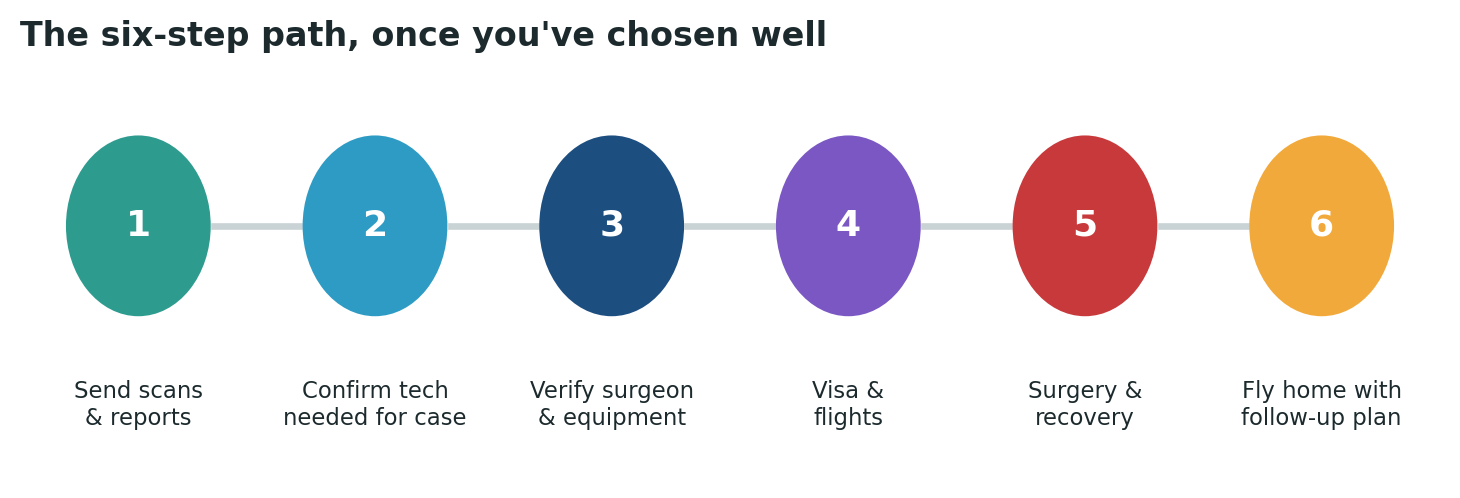
- For Congolese patients, the guide recommends sending actual scan files, maintaining a 15–20% financial buffer, arranging the paper medical and attendant visas early and carrying a current yellow-fever certificate. The page 4 pathway covers scan review, confirming whether advanced technology is needed, verifying the surgeon and equipment, arranging travel, undergoing surgery and returning home with a follow-up plan.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
- Treatment
- Neuronavigation-Assisted Brain Surgery
- Patients
- Congolese Patients
- Key Specialist
- Eloquent-Area / Functional Neurosurgery Sub-Specialist
- Decision Weighting
- Surgeon 50% / Hospital & Technology 50%
- First Step
- Confirm whether advanced technology is genuinely required
- Critical Areas
- Speech, movement, vision and memory
- Surgeon Check
- Exact-lesion case volume during the previous 12 months
- Qualification
- MCh/DNB Neurosurgery plus relevant fellowship training
- Technology Check
- Neuronavigation routinely used in clinical practice
- Mapping
- Trained neurophysiologist for awake-craniotomy mapping when required
- Imaging
- Intraoperative MRI or CT when clinically indicated
- Critical Care
- Dedicated 24-hour neuro-ICU
- Accreditation
- NABH or JCI
- Cost Check
- Written, itemised estimate
- Financial Buffer
- 15–20% above written estimate
- Imaging Records
- Actual scan files
- Visa
- Paper medical visa and attendant visa
- Entry Requirement
- Current yellow-fever certificate
- Travel
- Connecting flights from Kinshasa to India
- Follow-Up
- Confirm post-treatment coordination before returning home
- Key Warning
- Do not rely on equipment being merely listed on a hospital website
- Decision Principle
- Verify both the specialist's expertise and the technology's availability for the specific operation.
In Brief
For Congolese patients considering advanced brain surgery in India, the guide recommends confirming that neuronavigation genuinely benefits the specific case before selecting a centre. Patients should then verify an eloquent-area sub-specialist, exact-lesion experience, technology availability for the scheduled operation, neurophysiology and neuro-ICU support, along with written costs and follow-up arrangements.
First, Confirm Your Case Actually Needs This
Not every brain lesion requires neuronavigation or awake-craniotomy mapping. A tumour in an accessible location, away from speech, movement, or vision pathways, can often be handled safely by a skilled surgeon without this technology — and paying for it, or travelling further to get it, adds cost without adding benefit. This guide is for the cases where the lesion sits close to or within an eloquent area, where the technology genuinely changes the risk profile of the operation.
A straightforward way to think about this: if your surgeon cannot point to the specific brain function at risk in your case — speech, movement, vision, memory — and explain why standard surgery alone would carry meaningful risk to it, the advanced technology conversation may not be necessary for your case at all.
Two Decisions, Not One
For advanced-technology cases, the decision splits close to evenly between the surgeon's own skill and judgement, and the hospital's genuine, verified access to the equipment and support staff the operation needs. A brilliant surgeon without functioning neuronavigation on the day of your surgery is no better off than a well-equipped hospital without the sub-specialist to use it properly. Neither half of this decision substitutes for the other, and a family focused only on "does the hospital have the machine" risks missing the surgeon-side questions that matter just as much.
Part One: Choosing the Surgeon
- A named sub-specialist in eloquent-area surgery — not a general neurosurgeon who occasionally uses navigation equipment.
- Case volume in this exact lesion location, in the last 12 months — surgery near the speech centre and surgery near the motor cortex demand different, specific experience.
- An honest answer on whether your case actually needs this technology — a surgeon willing to say "you don't need this" is more trustworthy than one who upsells it universally.
- Qualification verified against the ladder below, not just a title on a website or brochure.
| Stage | What it means |
|---|---|
| MBBS | Basic medical degree — the entry point, not evidence of advanced surgical skill on its own. |
| MS (General Surgery) | Three years' surgical foundation training, required before most neurosurgery super-specialisation. |
| MCh / DNB Neurosurgery | The core neurosurgery qualification — three to six years of dedicated cranial and spinal surgical training. |
| Fellowship in skull-base / functional neurosurgery | Additional dedicated training in eloquent-area and image-guided surgery — the credential that actually confirms hands-on experience with this specific technology, distinct from owning the equipment. |
A hospital can own a neuronavigation system without every surgeon on staff being genuinely trained to operate with it as a routine part of their practice. The fellowship line on this ladder is where that distinction becomes verifiable — ask specifically whether the surgeon's fellowship training included image-guided or eloquent-area surgery, rather than assuming a senior title covers it.
Part Two: Verifying the Hospital and Technology
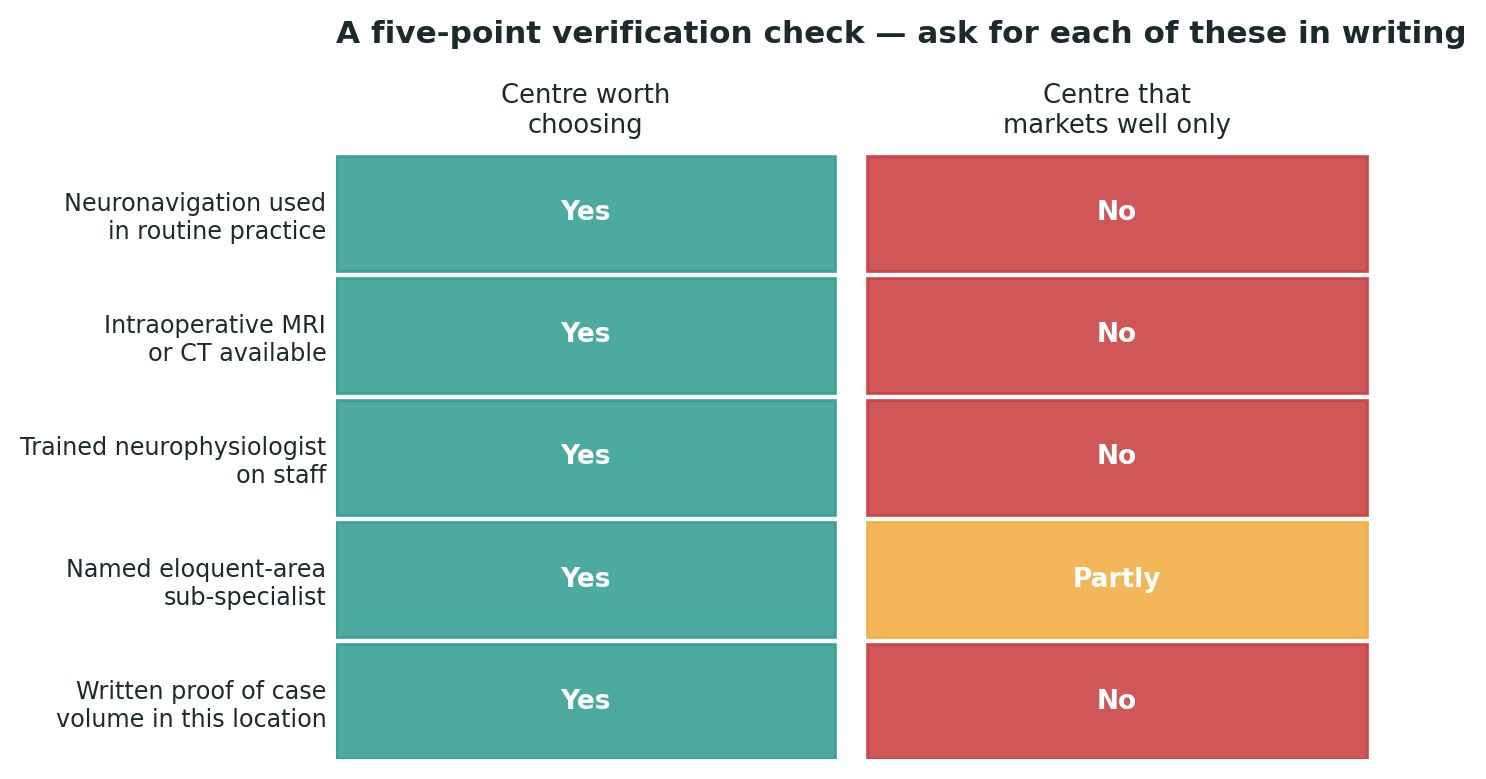
This is the part most families cannot judge from a brochure alone, which is exactly why it needs direct, specific questions rather than general reassurance. The five points below are the practical checklist behind that verification.
- Neuronavigation actually used for routine cases, not equipment purchased but rarely operated, sitting unused in a back room.
- A trained neurophysiologist on staff if awake-craniotomy mapping is part of your plan — the equipment alone is not enough without this expertise.
- Intraoperative MRI or CT genuinely on site, if your case calls for it, rather than a claim that turns out to mean a scanner elsewhere in the city.
- A dedicated neuro-ICU with 24-hour cover, since complications after this kind of surgery can develop within hours.
- NABH accreditation in India, or JCI internationally, auditing patient safety and clinical governance, not just equipment lists.
What the quote doesn't always show
In 24 years of reviewing these estimates, I have found the disputes almost never concern the headline number — they concern what it silently left out: neuronavigation listed as "available" but charged as an add-on, or not actually scheduled for the operating slot booked. Get written confirmation that the specific technology will be used in your operation, not just that the hospital owns it, and never pay the full balance before surgery.
It is worth saying plainly that this level of scrutiny is not paranoia — it reflects how the equipment itself works in practice internationally. Even well-resourced hospitals sometimes have a single navigation system shared across several operating theatres, meaning availability on paper does not guarantee availability on your specific surgery date. Asking the question in advance, in writing, is a normal and expected part of planning this kind of surgery, not an unusual demand.
What a Congolese Patient Should Weigh in Particular
Beyond verifying the surgeon and the technology, a handful of practical realities specific to travelling from the DRC deserve their own attention.
Send scan files, not just typed reports, to every centre being compared — surgical planning for eloquent-area cases depends on the precise imaging, more than for most other neurosurgery.
Currency and budget. The Congolese franc has weakened considerably against the dollar (roughly CDF 2,300–2,350 per US$1 in mid-2026, and it moves), and Indian hospitals quote and expect payment in dollars. Budget with a 15–20% margin above the written estimate.
Visa timing. DRC passport holders need a paper medical visa, not an e-visa, through the Embassy of India in Kinshasa (Avenue Batetela, Gombe), typically taking around two weeks once the hospital's invitation letter is ready. Apply for the attendant visa for a companion in the same batch.
Yellow fever certificate, current and dated at least 10 days before travel — the DRC is yellow fever-endemic and India requires proof at entry.
No direct flight. Ethiopian Airlines via Addis Ababa is the most frequent route from Kinshasa; Kenya Airways, Air France, and Qatar Airways offer workable alternatives, at roughly 16 to 20 hours total.
Four signals that should make you pause
- Technology mentioned in marketing but not confirmed in writing for your specific operation.
- No willingness to explain honestly whether your case needs this level of technology at all.
- No named sub-specialist with documented eloquent-area case volume.
- Pressure to pay the full balance before a written surgical plan exists.
| Ask the surgeon | Ask the hospital |
|---|---|
| Will neuronavigation actually be used in my operation? | Is the equipment scheduled for my specific surgery date? |
| How many cases in this exact location this year? | Who operates and maintains the navigation system? |
| Do you have a neurophysiologist for mapping, if needed? | Who coordinates my follow-up care once I'm home? |
Send these two short lists in writing, by email, before agreeing to travel. A centre confident in its own capability will answer both directly, with specifics; one that responds only with general reassurance about being "fully equipped" is telling you something too.
A closing word
Advanced technology only helps if it is genuinely, verifiably part of your specific operation — not a line on a brochure or a machine purchased once and rarely used since. A named sub-specialist backed by equipment confirmed in writing for your exact surgery date is the baseline worth insisting on before any deposit is paid, and no reputable centre will hesitate to provide that confirmation when asked directly. If you can share your scans and any quotes you've already received, I am glad to review them honestly, including telling you if a proposed centre's claims do not hold up to scrutiny, or if your case does not need this level of technology at all.
Sources
- 🌐 National Medical Commission of India — verify any surgeon's registration · nmc.org.in
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH) · nabh.co
- 🌐 Embassy of India, Kinshasa — medical visa requirements · eoikinshasa.gov.in
- 🌐 Effects of neuronavigation on glioma surgery outcomes, cohort study · pubmed.ncbi.nlm.nih.gov/38734167
- 🌐 World Health Organization — yellow fever vaccination requirements · who.int/health-topics/yellow-fever
Frequently Asked Questions by Congolese Patients about Selecting the Best Neuronavigation-Capable Surgeons and Hospitals in India
Does every brain surgery require neuronavigation?
No. The guide explains that accessible lesions away from speech, movement, vision or memory pathways may not require this technology. The need should be determined from the individual case.
How are the surgeon and hospital weighted?
The page 2 graphic assigns 50% to the surgeon and 50% to hospital/technology, showing that neither specialist expertise nor equipment should be considered in isolation.
What type of surgeon should I choose?
Look for a named sub-specialist in eloquent-area surgery, rather than a general neurosurgeon who only occasionally uses neuronavigation.
How should I check the surgeon's experience?
Ask how many operations involving the exact lesion location the surgeon has performed during the previous 12 months. Surgery near the speech centre and motor cortex requires different experience.
What qualifications should I verify?
The guide recommends checking the surgeon's MCh/DNB Neurosurgery qualification and relevant fellowship training, particularly whether the fellowship included image-guided or eloquent-area surgery.
Why is a neurophysiologist important?
If awake-craniotomy mapping is planned, the guide recommends confirming that a trained neurophysiologist is available, because the equipment alone does not provide the necessary expertise.
Should intraoperative MRI or CT be available?
When the case requires it, the guide recommends confirming that intraoperative MRI or CT is genuinely on site, rather than relying on a scanner located elsewhere in the city.
What should I confirm about the technology?
Ask whether neuronavigation will actually be used during your operation, whether it is scheduled for your specific surgery date and who operates and maintains the system.
What should the quotation include?
The written estimate should clearly state whether neuronavigation and other required technology are included in the procedure or charged separately. Patients should never rely only on a hospital's general equipment list.
What are the main warning signs?
Pause if the technology is only mentioned in marketing, the surgeon cannot explain whether your case actually needs it, there is no named sub-specialist with documented lesion-specific experience or you are pressured to pay the full balance before a written surgical plan exists.
Page Summary
This guide helps Congolese patients select neuronavigation-capable surgeons and hospitals in India by separating the need for advanced technology from the choice of specialist and centre. The page 2 graphic assigns 50% to the surgeon and 50% to hospital/technology, while the page 3 chart places the highest weight on confirmed use of neuronavigation for the actual operation, eloquent-area expertise, lesion-specific experience and neurophysiology support. The page 4 pathway adds practical guidance on imaging, travel, visas, surgery and follow-up.
Citation Block
| Field | Information |
|---|---|
| Topic | Selecting Neuronavigation-Capable Surgeons and Hospitals in India for Congolese Patients |
| Treatment | Neuronavigation-Assisted Brain Surgery |
| Patients | Congolese Patients |
| Key Specialist | Eloquent-Area / Functional Neurosurgery Sub-Specialist |
| Decision Weighting | Surgeon 50% / Hospital & Technology 50% |
| Technology Indication | Lesions near speech, movement, vision or memory pathways |
| Surgeon Criteria | Sub-specialisation and exact-lesion case volume |
| Qualification | MCh/DNB Neurosurgery plus relevant fellowship |
| Neuronavigation | Confirmed use during the patient's specific operation |
| Neurophysiology | Trained neurophysiologist for awake-craniotomy mapping |
| Imaging | Intraoperative MRI or CT when required |
| Critical Care | Dedicated 24-hour neuro-ICU |
| Accreditation | NABH or JCI |
| Cost Transparency | Written, itemised estimate |
| Imaging | Actual scan files |
| Financial Planning | 15–20% buffer above written estimate |
| Visa | Paper medical visa and attendant visa |
| Entry Requirement | Yellow-fever certificate |
| Travel | Connecting flights from Kinshasa |
| Follow-Up | Post-treatment coordination |
| Warning Signs | Technology mentioned only in marketing, no named sub-specialist, no case-volume evidence or advance-payment pressure |
| Key Decision | Verify that the right specialist and functioning technology are both available for the specific operation |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Congo





Ready to Take the First Step?
Share your medical reports with our healthcare managers today and receive a FREE CONSULTATION, a personalized treatment plan and complete support from your arrival to your recovery.
Get Your Free ConsultationAreas We Serve
At Indian Health Guru Consultants, we proudly assist patients from Congo and neighboring countries across Central, East and Southern Africa who travel to India for advanced medical treatment. Our experienced international patient team provides end-to-end support, including medical opinions, hospital selection, Medical Visa assistance, travel planning, accommodation, interpreter services and post-treatment follow-up.
We regularly serve patients from:
- Gabon
- Cameroon
- Angola
- Uganda
- Rwanda
- Burundi
- Tanzania
- Zambia
- Djibouti
- Comoros
- Madagascar
- Seychelles
- South Sudan
- Central African Republic
- Republic of the Congo
- Democratic Republic of the Congo
No matter where you are located in the region, Indian Health Guru Consultants is committed to making your medical journey to India safe, affordable, seamless and completely patient-focused.
From Congo to India: Your Complete Patient Guide
- Brain Tumor Surgery in India for Congolese Patients
- Best Brain Tumour Surgeons & Hospitals in India for Congo Patients
- Knee Replacement in India for Congolese Patients
- Best Knee Replacement Surgeons & Hospitals in India for Congolese Patients
- Spine Surgery in India for Congolese Patients
- Best Spine Surgeons & Hospitals in India for Congolese Patients
- Liver Transplant in India for Congolese Patients: Cost & Guide
- Best Liver Transplant Centres and Hospitals in India for Congolese Patients
- Cardiac Surgery in India for Congolese Patients: Cost & Guide
- Best Cardiac Surgeons & Hospitals in India for Congolese Patients
- Bone Marrow Transplant in India for Congolese Patients: Cost & Guide
- Best Bone Marrow Transplant Centres and Hospitals in India for Congolese Patients
- Prostate Cancer Treatment in India for Congolese Patients: Cost & Guide
- Best Prostate Cancer Centres and Hospitals in India for Congolese Patients
- HIPEC in India for Congolese Patients: Cost & Treatment Guide
- Best HIPEC Centres and Hospitals in India for Congolese Patients
- Kidney Transplant in India for Congolese Patients: Cost & Guide
- Best Kidney Transplant Centres and Hospitals in India for Congolese Patients