

Heart Failure Treatment in India for Congolese Patients: What It Costs, and How to Decide Well
A practical guide for Congolese patients understanding heart failure treatment in India, including diagnosis, advanced device therapy, costs and long-term follow-up.
Heart failure carries a fairly fixed image for many people: an elderly patient, decades of narrowed arteries, a slow decline in the seventies or eighties. In 24 years of advising patients on cardiac conditions, I have found that this image fits Congolese heart failure patients far less often than it fits patients in Europe or North America — and understanding why changes how urgently a family should act, and what kind of treatment genuinely fits the situation. This guide sets out plainly what a real DRC study found, what advanced heart failure treatment in India costs against the Western alternatives some patients consider, and what to weigh before deciding. None of this is meant to cause alarm — it is meant to correct an assumption that can otherwise delay a proper diagnosis.
Healing Journeys of Congolese Patients







Key Takeaways
- The guide explains that heart failure affects Congolese patients at a considerably younger age than the typical Western patient. A Lubumbashi study found an average patient age of 56 years, highlighting why persistent breathlessness, swelling and unusual fatigue in younger adults should not automatically be dismissed as unrelated problems.
- The page 2 graphic shows a different underlying disease pattern: dilated cardiomyopathy accounted for 48% of DRC cases compared with 15% in the typical West, while ischaemic coronary disease accounted for only 4% compared with 60% in the West. This distinction matters because cardiomyopathy may require medication optimisation and, in advanced cases, device therapy rather than treatment focused primarily on restoring coronary blood flow.
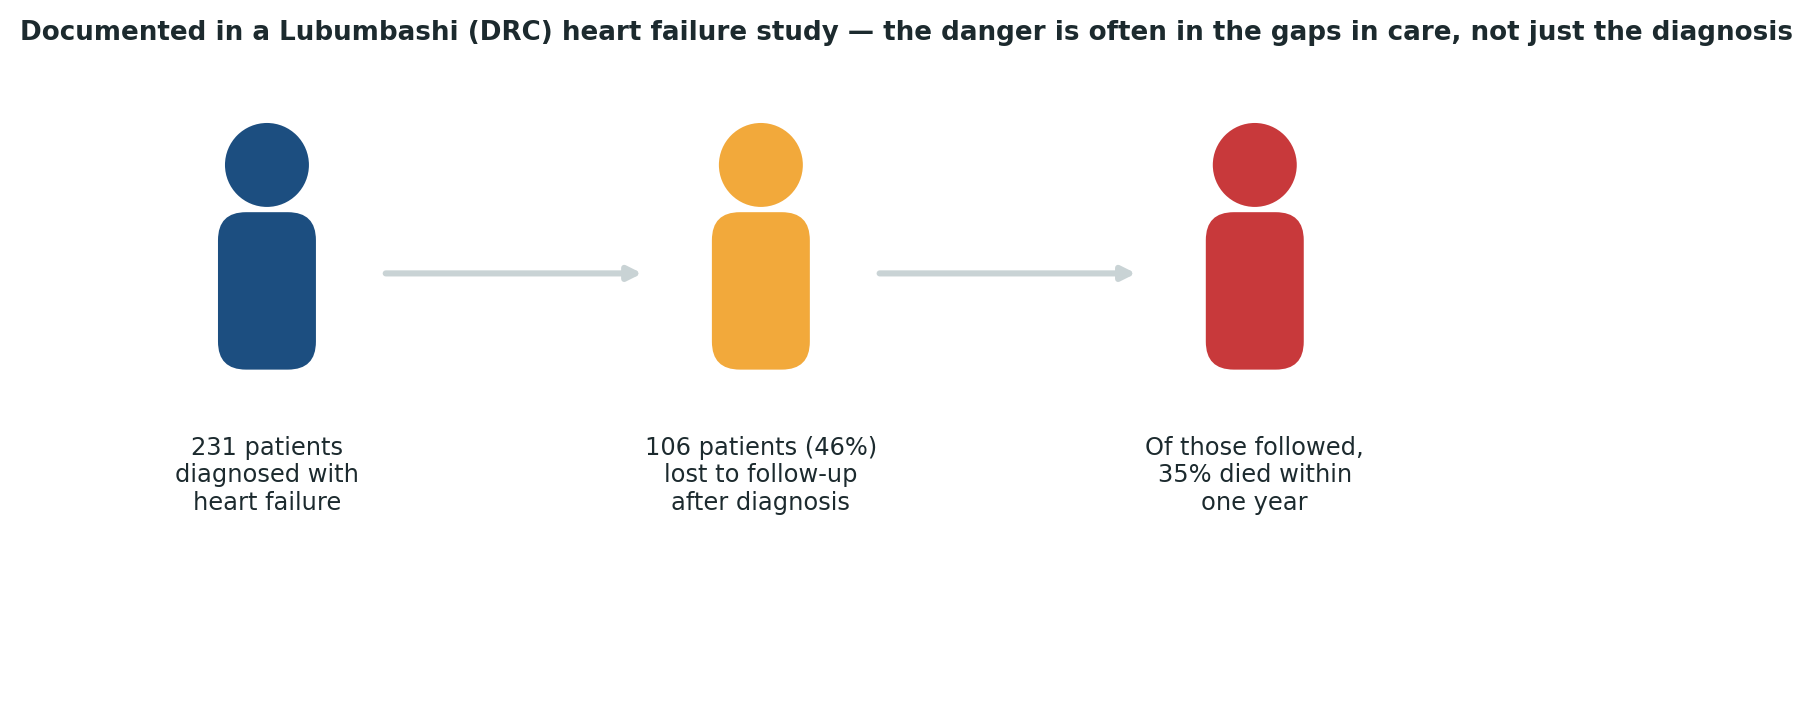
- The guide highlights that follow-up is a major challenge, not simply diagnosis. In the cited Lubumbashi study, 46% of 231 patients were lost to follow-up, and among those who remained in follow-up, 35% died within one year. The guide therefore stresses that medication adjustment, monitoring and a structured plan after returning home are as important as the initial treatment.
- The page 4 cost graphic gives an indicative CRT device implantation cost of US$6,000–18,000 in India, compared with US$20,000–38,000 in France/Belgium, US$25,000–51,000 in the UK private sector and US$50,000–100,000 in the US. The guide recommends confirming whether the proposed device is CRT-P or CRT-D and what structured follow-up and medication optimisation are included.
- For Congolese patients, the guide recommends echocardiogram-based assessment, sending actual cardiac test results and imaging, confirming whether medication can be optimised before device therapy, and arranging structured follow-up before travelling. It also recommends a 15–20% financial buffer, early medical and attendant visa preparation, a current yellow-fever certificate and identification of a doctor in the DRC for ongoing care.
- The guide identifies four warning signs: device therapy recommended without genuine echocardiogram-based evaluation, no discussion of medication optimisation, no structured follow-up plan and pressure to pay the full balance before receiving a written treatment plan.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
- Treatment
- Heart Failure Treatment
- Patients
- Congolese Patients
- Key Specialist
- Heart Failure / Cardiology Specialist
- First Step
- Echocardiogram-based cardiac evaluation
- Key Condition
- Dilated cardiomyopathy
- DRC Study Age
- Average patient age 56 years
- Key Follow-Up Finding
- 46% lost to follow-up in the cited study
- Advanced Therapy
- Cardiac Resynchronization Therapy (CRT)
- Device Options
- CRT-P and CRT-D
- India CRT Cost
- US$6,000–18,000 indicative range
- Cost Check
- Device, implantation and structured follow-up
- Financial Buffer
- 15–20%
- Second Opinion
- Recommended where appropriate
- Visa
- Paper medical visa and attendant visa
- Entry Requirement
- Current yellow-fever certificate
- Follow-Up
- Named doctor in the DRC
- Key Warning
- Do not proceed with device therapy without proper cardiac assessment
- Decision Principle
- Choose a treatment plan that combines accurate diagnosis, appropriate therapy and reliable long-term follow-up.
In Brief
For Congolese patients considering heart failure treatment in India, the guide recommends prioritising accurate diagnosis, appropriate medication optimisation and continuity of care. Patients should confirm the cause and severity of heart failure, establish whether CRT or another advanced treatment is appropriate, obtain transparent costs and arrange long-term follow-up in the DRC.
A Disease of Younger Adults, Not the Elderly
A detailed study of heart failure patients treated at a private and a university hospital in Lubumbashi, DRC, found an average patient age of 56, with a considerable spread either side. This stands in sharp contrast to high-income countries, where heart failure is overwhelmingly a disease of patients in their seventies and eighties.
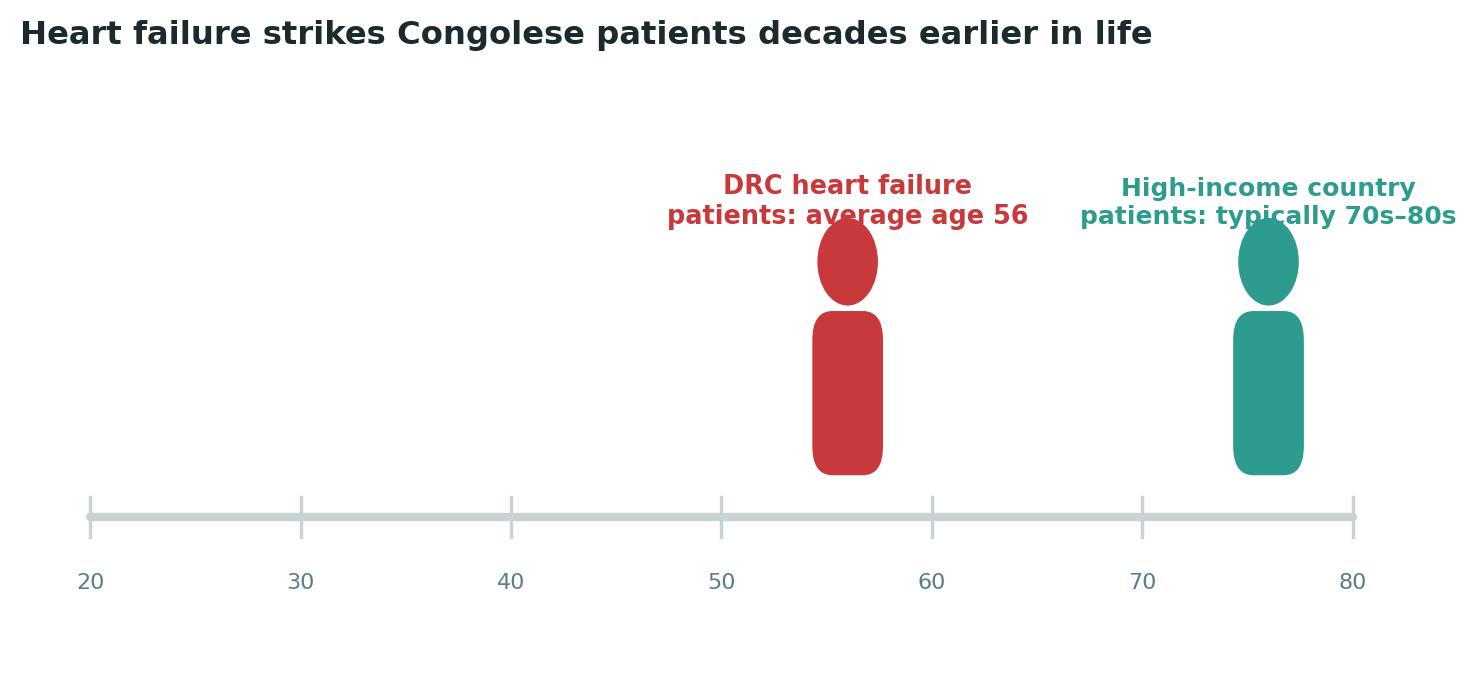
This matters enormously for how families and employers think about the condition. A 56-year-old Congolese patient with heart failure is very often still the primary income earner for their household, making both the human and economic stakes of delayed or inadequate treatment considerably higher than the typical Western case.
A Different Cause Behind the Same Diagnosis
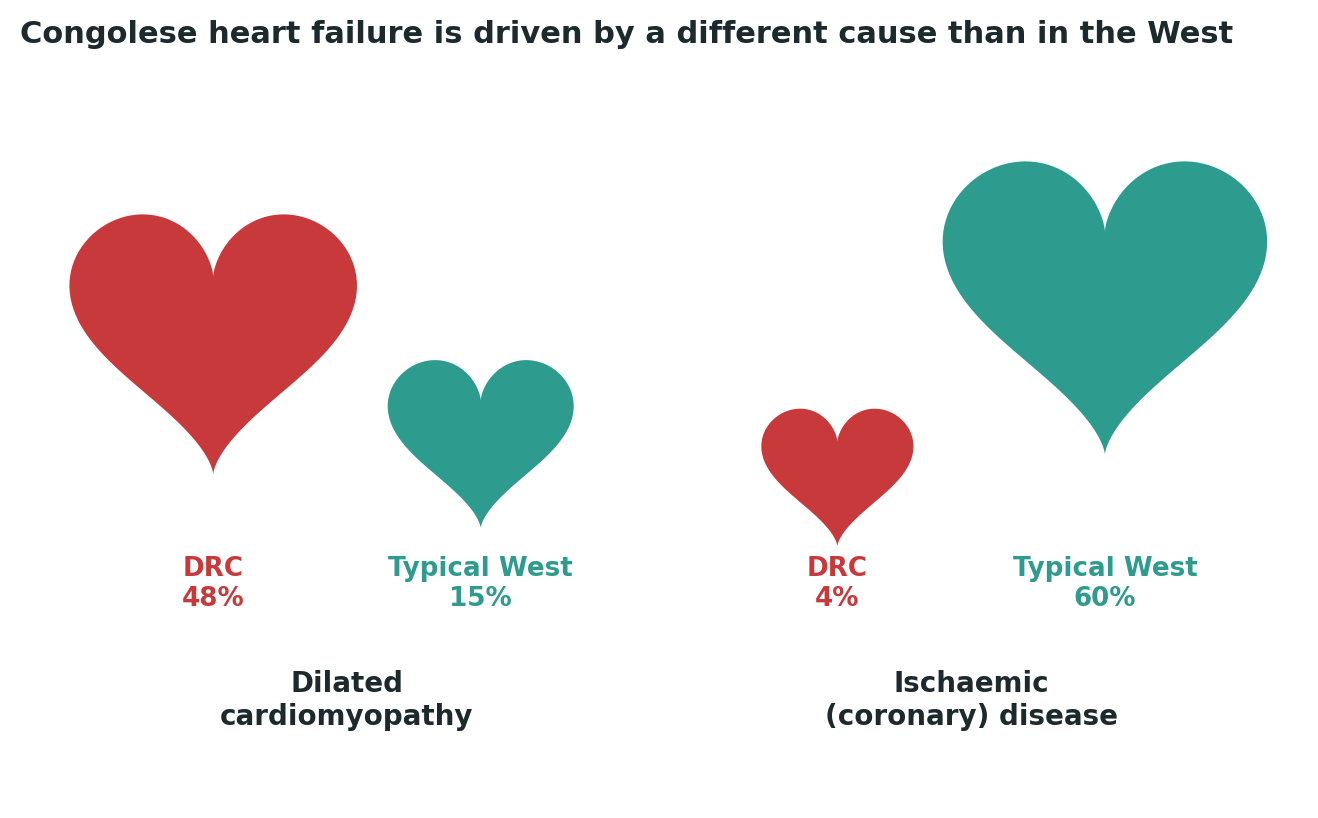
The same Lubumbashi study found that dilated cardiomyopathy, a weakening and enlargement of the heart muscle itself, was the most common underlying cause of heart failure, present in nearly half of all cases. Ischaemic heart disease, caused by narrowed coronary arteries and the dominant cause of heart failure in high-income countries, was present in only a small fraction of DRC cases.
This distinction matters for treatment planning, not just curiosity. Ischaemic heart failure often responds well to procedures that restore blood flow to the heart muscle, such as bypass surgery or stenting. Dilated cardiomyopathy, by contrast, usually calls for a different combination of medication, careful monitoring, and, in more advanced cases, device-based therapy — treating it as though it were ischaemic disease would miss the actual problem.
The leading documented risk factors in the same study were hypertension, present in well over half of patients, followed by chronic kidney disease, alcohol-related heart damage, and obesity. This pattern points toward a condition that, in many cases, develops from a combination of poorly controlled blood pressure and other manageable risk factors — treatable and, to a real degree, preventable, if caught and managed consistently.
The one fact worth remembering
Persistent breathlessness, swelling in the legs or abdomen, and unusual fatigue in a relatively young adult are not automatically something else — in the DRC specifically, these are the classic presentation of heart failure at an age Western medical intuition might not expect. This is worth raising directly and specifically with a doctor, rather than assuming heart failure is unlikely simply because of age.
Why the Gaps in Follow-Up Care Matter as Much as the Diagnosis
Perhaps the most sobering finding from the same study was not about diagnosis at all, but about what happened afterward. Nearly half of patients were lost to follow-up after their initial diagnosis, a pattern the researchers linked to lack of organised care, poverty, and limited health literacy. Among those who were followed, over a third died within a year of presentation.
This finding is arguably more important for a family planning treatment than the diagnosis itself. It suggests that even excellent initial treatment, wherever it happens, can be undermined afterward if there is no clear, structured plan for ongoing monitoring, medication adjustment, and follow-up visits once the patient returns home.
What Advanced Treatment Costs: DRC Reality vs India vs the West
For patients whose heart failure does not respond adequately to medication alone, a cardiac resynchronization therapy (CRT) device can meaningfully improve symptoms and survival by helping the heart's chambers beat in a more coordinated way. Cost varies with the specific device type, but the relative gap between India and Western options holds fairly consistently.
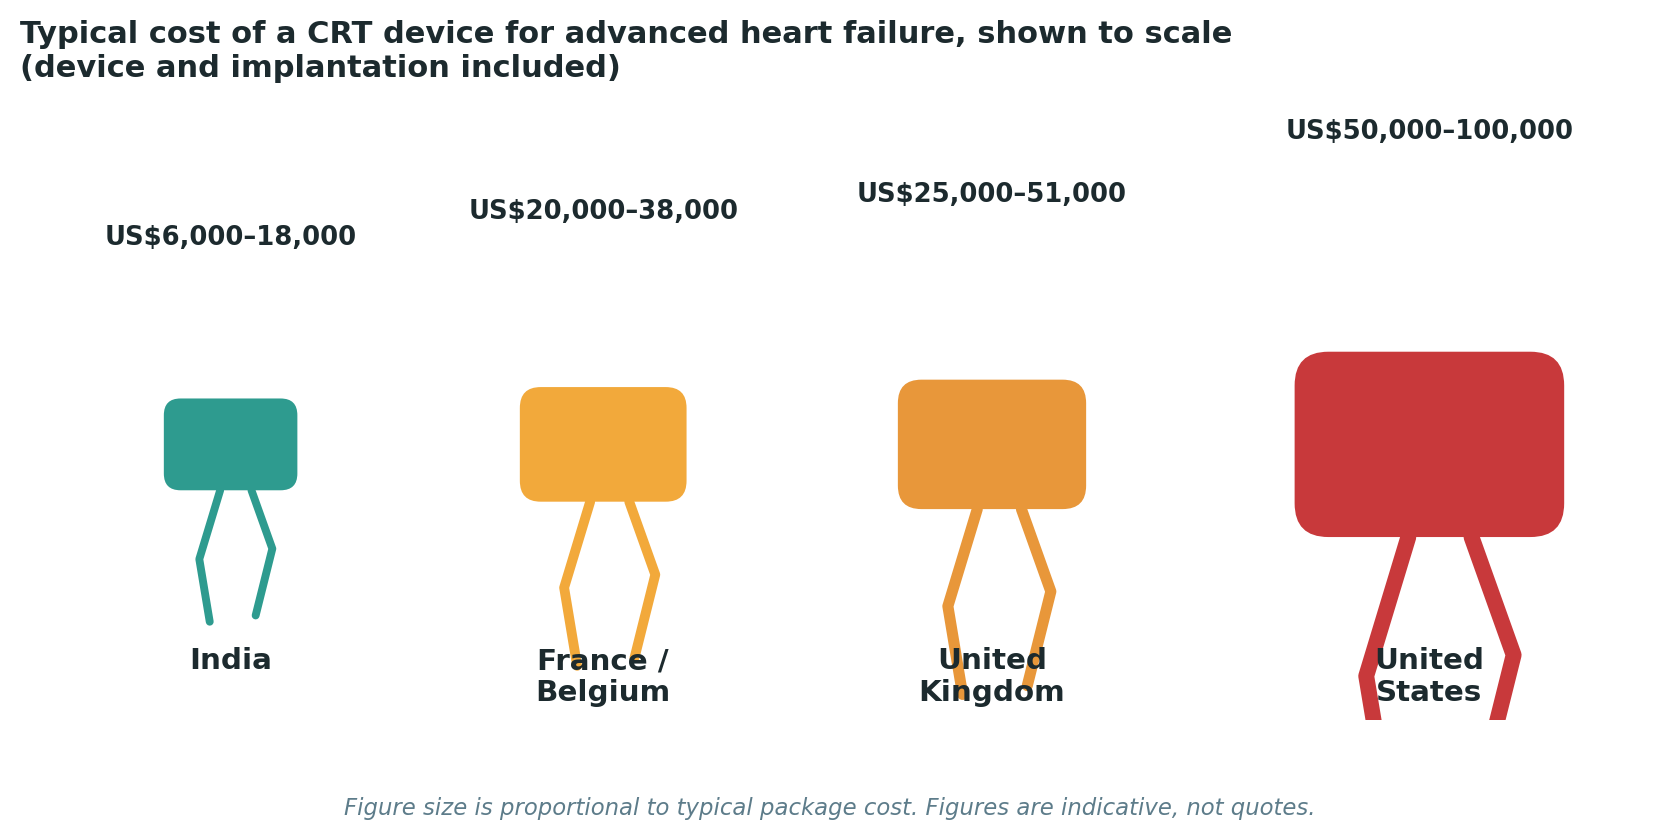
In India, a CRT device implant typically costs US$6,000 to US$18,000. In France or Belgium, private-sector costs typically run US$20,000 to US$38,000. In the UK's private sector, costs range roughly US$25,000 to US$51,000. In the US, the same procedure commonly costs US$50,000 to US$100,000. India's typical price sits at roughly a tenth of the uninsured US figure.
What the number on the quote does not always show
A written estimate should specify the exact device type (CRT-P or CRT-D, which adds defibrillator capability), and what structured follow-up and medication optimisation is included afterward. In 24 years of reviewing these quotes, I have found disputes almost never concern the headline figure — they concern what it silently left out. Get every line item in writing, and never pay the full balance before treatment.
What a Congolese Patient Should Weigh, Specifically
- Get a genuine echocardiogram-based evaluation, establishing the exact cause and severity of your heart failure before any treatment plan is finalised.
- Ask specifically whether medication alone might still be optimised further, or whether device therapy is genuinely warranted for your case.
- Arrange a clear, structured follow-up plan before you travel — the DRC data makes plain that ongoing care matters as much as the initial treatment.
- Send the actual test results and imaging, not just a description of symptoms, since treatment planning depends on precise cardiac assessment.
- Budget in US dollars, with margin. The Congolese franc has weakened considerably against the dollar (roughly CDF 2,300–2,350 per US$1 in mid-2026, and it moves); build in a 15–20% buffer above the initial estimate.
- Start the visa process early. DRC passport holders need a paper medical visa through the Embassy of India in Kinshasa (Avenue Batetela, Gombe), typically around two weeks once the hospital's invitation letter is ready; apply for an attendant visa at the same time.
- Confirm your yellow fever certificate is current — mandatory for entry into India, at least 10 days before travel.
- Identify a doctor at home who will manage your ongoing follow-up before you fly, given how much the DRC data shows this specific step matters.
Four signals that should make you pause
- A device recommended without a genuine echocardiogram-based evaluation.
- No discussion of whether medication optimisation has been fully explored first.
- No structured follow-up plan discussed before treatment.
- Pressure to pay the full balance before a written treatment plan exists.
Why India Specifically for Heart Failure Treatment for Congolese Patients?
India operates high-volume heart failure centres with genuine experience across both medication optimisation and device-based therapy, treating the same pattern of relatively young-onset, non-ischaemic heart failure that is common domestically in India and closely mirrors what Congolese patients typically present with. Combined with English-language consultation throughout and hospital accreditation (NABH domestically, JCI internationally) that mirrors the standards used to evaluate hospitals in the US and Europe, India offers a depth of relevant experience and a structured approach to follow-up that directly addresses the gap the DRC's own data shows matters most, for a condition where consistent care over years, not just a single successful procedure, ultimately determines the outcome.
A closing word
Heart failure in a Congolese patient in their forties or fifties is not a medical anomaly — it is, unfortunately, closer to the norm, and it deserves to be taken as seriously as it would be at any age. What matters most is a proper diagnosis, a genuinely considered treatment plan, and a structured follow-up arrangement that does not let the patient fall through the cracks. If you are able to share your test results, I am glad to give a direct, honest view on what your case would involve.
Sources
- 🌐 National Medical Commission of India — verify any surgeon's registration · nmc.org.in
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH) · nabh.co
- 🌐 Embassy of India, Kinshasa — medical visa requirements · eoikinshasa.gov.in
- 🌐 "Heart Failure Etiologies and Challenges to Care in the Developing World: An Observational Study in the Democratic Republic of Congo," Journal of Cardiac Failure (2018) · onlinejcf.com
- 🌐 "Heart failure in Africa: challenges of dealing with a heterogeneous syndrome," European Heart Journal (2023) · academic.oup.com/eurheartj
- 🌐 World Health Organization — yellow fever vaccination requirements · who.int/health-topics/yellow-fever
Frequently Asked Questions by Congolese Patients about Heart Failure Treatment in India
At what age did heart failure patients present in the cited DRC study?
The Lubumbashi study found an average patient age of 56 years, considerably younger than the typical age of presentation in high-income countries.
What was the most common cause of heart failure in the DRC study?
Dilated cardiomyopathy accounted for 48% of cases, making it substantially more common than ischaemic heart disease in the cited DRC population.
Why does the cause of heart failure matter?
Different causes require different treatment approaches. Dilated cardiomyopathy may require medication optimisation, monitoring and potentially device therapy, rather than automatically treating the condition as coronary artery disease.
How serious is the follow-up gap?
The cited study found that 46% of 231 patients were lost to follow-up, while 35% of those who remained in follow-up died within one year.
What test should be completed before advanced treatment?
The guide recommends a genuine echocardiogram-based evaluation to establish the exact cause and severity of heart failure before finalising treatment.
When might CRT be considered?
The guide describes CRT as an option for patients whose heart failure does not respond adequately to medication alone, helping the heart's chambers beat in a more coordinated way.
What is the difference between CRT-P and CRT-D?
The quotation should clearly state whether the proposed device is CRT-P or CRT-D, with CRT-D adding defibrillator capability.
How much does a CRT implant cost in India?
The guide gives an indicative cost of US$6,000–18,000, including the device and implantation. Actual costs depend on the patient's condition and device choice.
Should medication be optimised before device therapy?
The guide recommends specifically asking whether medication alone can still be optimised or whether device therapy is genuinely warranted for the individual patient.
What should Congolese patients arrange before returning home?
Patients should establish a structured follow-up plan and identify a doctor in the DRC who can manage ongoing monitoring and medication adjustment after treatment in India.
Page Summary
This guide explains the distinct pattern of heart failure among Congolese patients, including younger age at presentation and the greater prevalence of dilated cardiomyopathy. The page 2 graphic compares DRC and Western causes, while the page 3 graphic highlights the substantial follow-up gap. Page 4 compares indicative CRT costs internationally and outlines the assessments, financial preparation, visa requirements and long-term follow-up that Congolese patients should consider.
Citation Block
| Field | Information |
|---|---|
| Topic | Heart Failure Treatment in India for Congolese Patients |
| Treatment | Heart Failure Management & Advanced Cardiac Therapy |
| Patients | Congolese Patients |
| Key Specialist | Heart Failure / Cardiology Specialist |
| First Assessment | Echocardiogram-based cardiac evaluation |
| Average DRC Patient Age | 56 years in the cited Lubumbashi study |
| Leading Cause | Dilated cardiomyopathy |
| DRC Dilated Cardiomyopathy | 48% in the cited study |
| DRC Ischaemic Disease | 4% in the cited study |
| Follow-Up Gap | 46% of 231 patients lost to follow-up |
| One-Year Mortality | 35% among those followed in the cited study |
| Advanced Therapy | Cardiac Resynchronization Therapy |
| Device Options | CRT-P and CRT-D |
| Indicative India Cost | US$6,000–18,000 |
| Cost Transparency | Device, implantation, follow-up and medication optimisation |
| Medical Records | Actual test results and cardiac imaging |
| Medication Review | Confirm whether medication can be optimised before device therapy |
| Financial Buffer | 15–20% |
| Second Opinion | Recommended where appropriate |
| Travel Documents | Paper medical and attendant visas |
| Entry Requirement | Current yellow-fever certificate |
| Follow-Up | Named doctor in the DRC before travel |
| Warning Signs | No echocardiogram-based assessment, no medication review or no structured follow-up |
| Key Decision | Establish the exact cause and severity of heart failure before choosing advanced treatment |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Congo





Ready to Take the First Step?
Share your medical reports with our healthcare managers today and receive a FREE CONSULTATION, a personalized treatment plan and complete support from your arrival to your recovery.
Get Your Free ConsultationAreas We Serve
At Indian Health Guru Consultants, we proudly assist patients from Congo and neighboring countries across Central, East and Southern Africa who travel to India for advanced medical treatment. Our experienced international patient team provides end-to-end support, including medical opinions, hospital selection, Medical Visa assistance, travel planning, accommodation, interpreter services and post-treatment follow-up.
We regularly serve patients from:
- Gabon
- Cameroon
- Angola
- Uganda
- Rwanda
- Burundi
- Tanzania
- Zambia
- Djibouti
- Comoros
- Madagascar
- Seychelles
- South Sudan
- Central African Republic
- Republic of the Congo
- Democratic Republic of the Congo
No matter where you are located in the region, Indian Health Guru Consultants is committed to making your medical journey to India safe, affordable, seamless and completely patient-focused.
From Congo to India: Your Complete Patient Guide
- Brain Tumor Surgery in India for Congolese Patients
- Best Brain Tumour Surgeons & Hospitals in India for Congo Patients
- Knee Replacement in India for Congolese Patients
- Best Knee Replacement Surgeons & Hospitals in India for Congolese Patients
- Spine Surgery in India for Congolese Patients
- Best Spine Surgeons & Hospitals in India for Congolese Patients
- Liver Transplant in India for Congolese Patients: Cost & Guide
- Best Liver Transplant Centres and Hospitals in India for Congolese Patients
- Cardiac Surgery in India for Congolese Patients: Cost & Guide
- Best Cardiac Surgeons & Hospitals in India for Congolese Patients
- Bone Marrow Transplant in India for Congolese Patients: Cost & Guide
- Best Bone Marrow Transplant Centres and Hospitals in India for Congolese Patients
- Prostate Cancer Treatment in India for Congolese Patients: Cost & Guide
- Best Prostate Cancer Centres and Hospitals in India for Congolese Patients
- HIPEC in India for Congolese Patients: Cost & Treatment Guide
- Best HIPEC Centres and Hospitals in India for Congolese Patients
- Kidney Transplant in India for Congolese Patients: Cost & Guide
- Best Kidney Transplant Centres and Hospitals in India for Congolese Patients