

Selecting the Best Heart Valve Replacement Surgeons and Hospitals in India: A Guide for Patients from Iraq
A doctor’s honest, question-by-question guide for patients from Iraq on vetting a heart valve hospital in India — transcatheter vs. surgical technique, accreditation, team composition, and the exact questions worth asking before you book anything.
Over the years, I have noticed that heart valve replacement has become genuinely more complicated to think through than it used to be, not because the surgery has gotten harder, but because there are now two fundamentally different ways to do it, open surgical replacement and transcatheter, minimally invasive replacement, and the right choice depends on specific factors about your heart and your age, not simply a preference for whichever sounds less invasive. In my experience of 24 years advising patients through exactly this decision, the honest starting point is that neither approach is universally better, and a hospital that recommends one over the other without a careful, individualised evaluation has skipped the most important step in your care.
Healing Journeys of Iraqi Patients







Key Takeaways
- Heart valve replacement now involves more than simply deciding whether surgery is needed. The source explains that patients may be considered for conventional surgical replacement or transcatheter replacement, and neither approach is universally superior. The appropriate choice depends on factors such as valve anatomy, age and overall surgical risk, making an individualised assessment more important than choosing the option that appears less invasive.
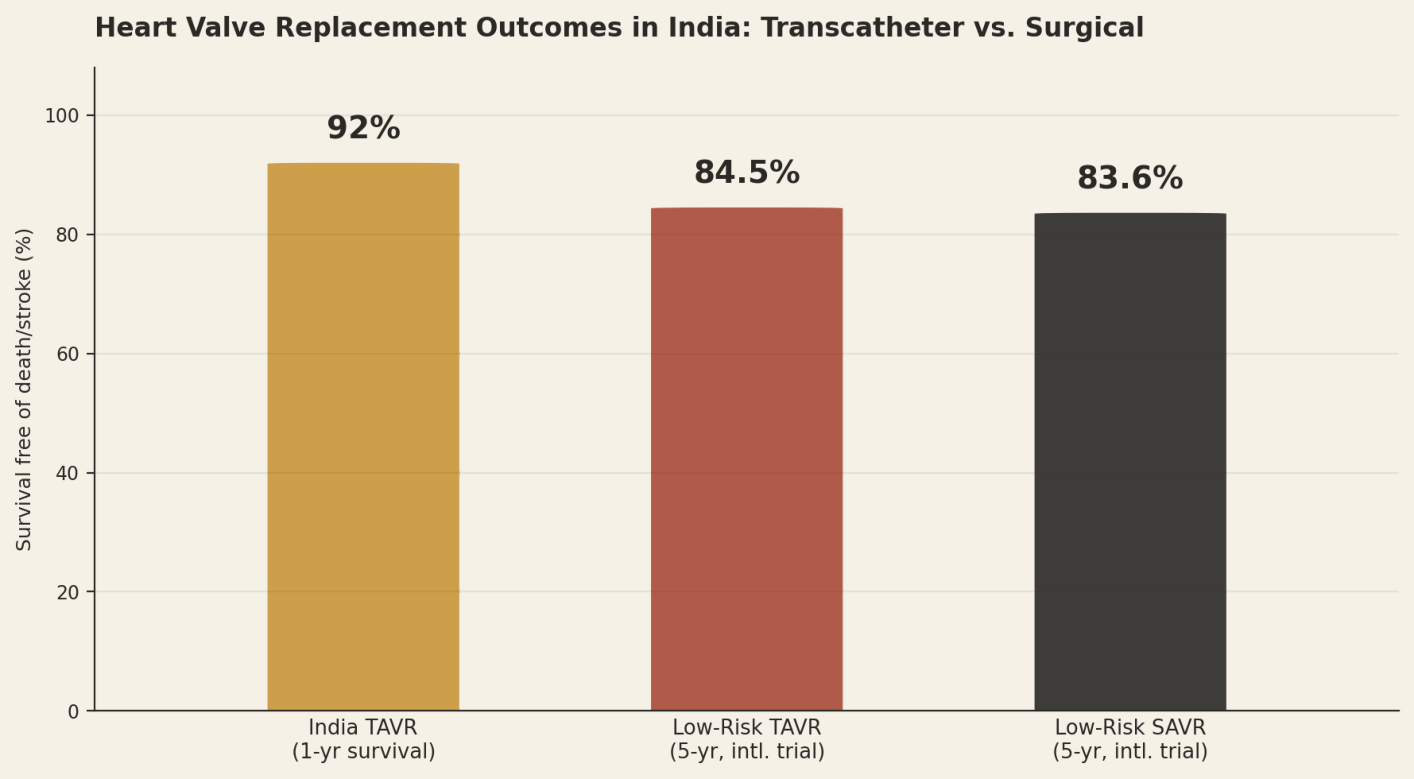
- The guide presents Indian and international outcome data to demonstrate why technique selection requires careful evaluation. An early Indian series of 25 TAVR patients reported 8% one-year all-cause mortality, with 80% of patients in good functional class at discharge and 16% requiring a permanent pacemaker. Another Indian series involving 84 intermediate- and high-risk patients reported procedural mortality of 2.3%. International low-risk trial data cited in the source showed five-year death or disabling stroke rates of 15.5% for transcatheter replacement and 16.4% for surgical replacement, without a statistically significant difference.
- The chart on page 2 visually compares 92% one-year survival for the cited Indian TAVR experience, 84.5% five-year survival for low-risk TAVR in the cited international trial and 83.6% for low-risk surgical aortic valve replacement. The guide labels these as illustrative figures and emphasises that neither technique should be considered universally superior.
- Accreditation and access to both treatment approaches are important when Iraqi patients evaluate hospitals in India. The guide recommends checking JCI and NABH accreditation and asking whether the hospital offers both transcatheter and surgical valve replacement under one roof. A genuine multidisciplinary heart team should be able to assess both options, rather than a hospital recommending the only technique it happens to provide.
- Patients should request procedure-specific outcome information rather than general statements about valve surgery. The source recommends asking for the centre's own procedural mortality and permanent pacemaker rate for transcatheter replacement, as well as asking how age and individual risk affect the expected long-term durability of each option. If a patient is eligible for either technique, the hospital should clearly explain which specific clinical factors led the heart team toward one approach.
- Heart valve replacement requires a multidisciplinary team, particularly when transcatheter treatment is being considered. The source identifies an interventional cardiologist experienced in transcatheter valve procedures, a cardiac surgeon for surgical treatment or backup, an imaging specialist to assess valve anatomy and sizing, and an anaesthesiologist experienced with both conscious sedation and general anaesthesia. The final recommendation should come from a genuine heart-team discussion rather than one specialist acting alone.
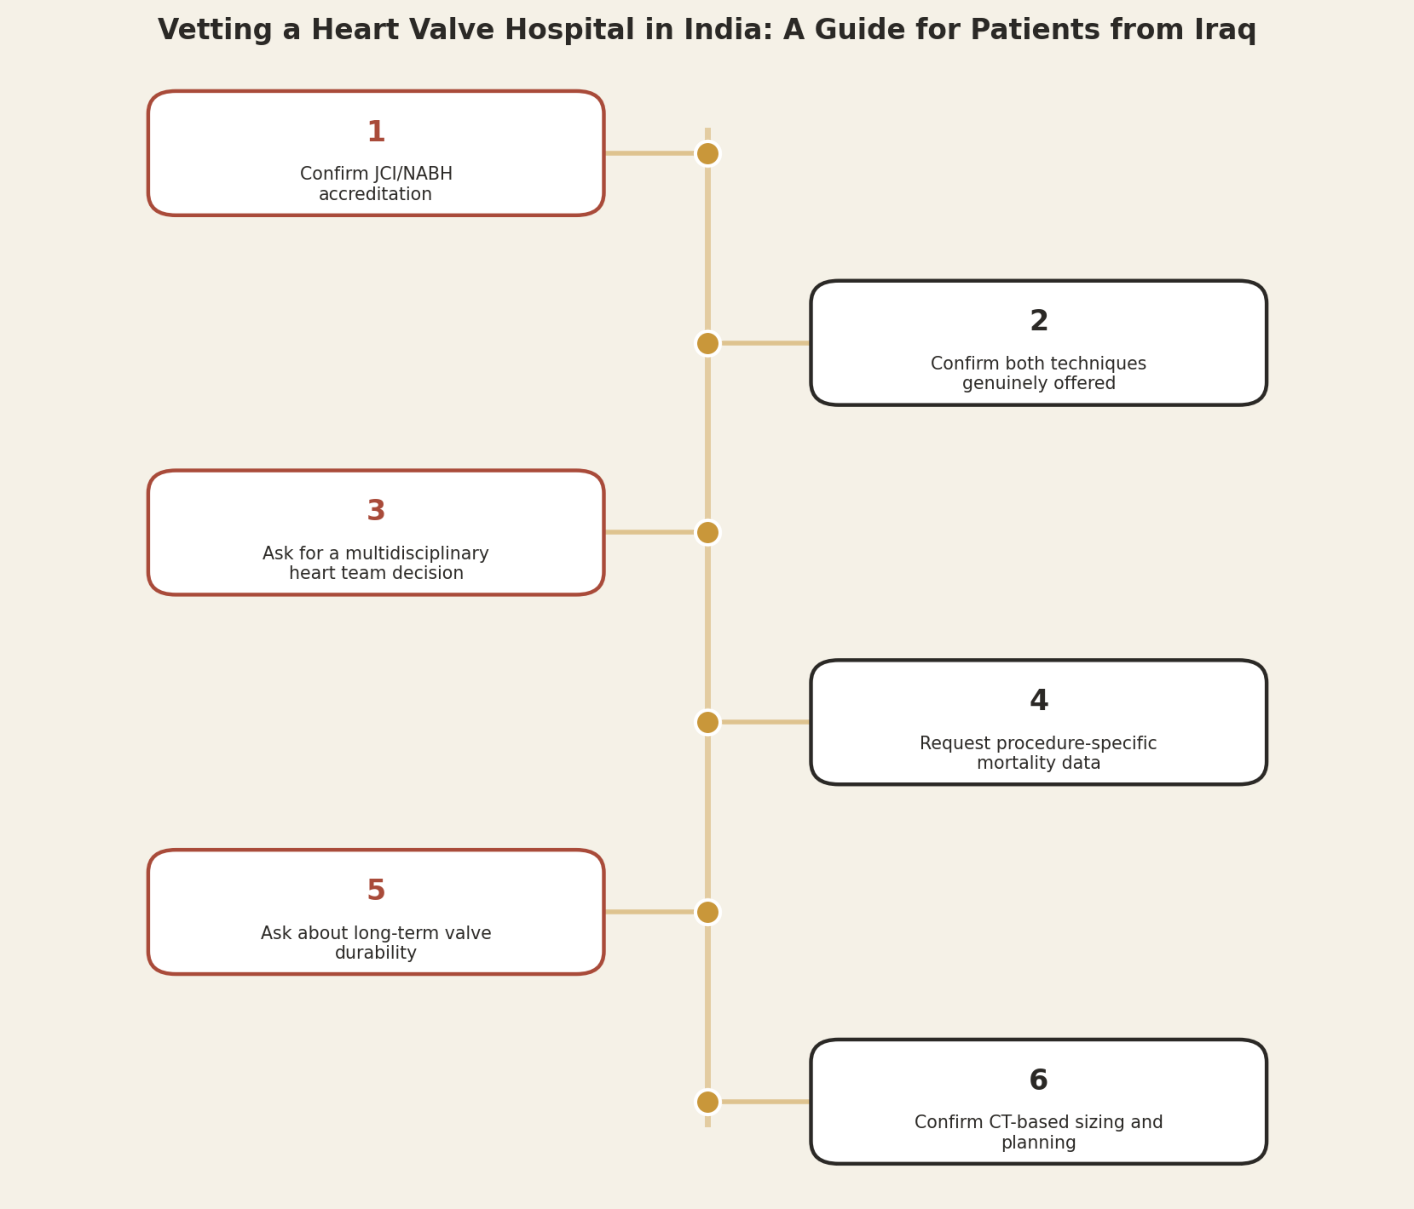
- The source identifies several warning signs: a hospital that provides only TAVR or only surgical replacement may have an inherent bias toward its available technique; centres that cannot provide procedure-specific mortality and complication data; centres that fail to discuss long-term valve durability in younger patients; and a transcatheter procedure planned without detailed pre-procedure CT imaging. The page 4 checklist highlights availability of both techniques, multidisciplinary heart-team decision-making, technique-specific outcome data and open discussion of long-term valve durability.
Quick Facts
- Treatment
- Heart valve replacement
- Primary Patients
- Iraqi patients seeking valve treatment in India
- Main Speciality
- Cardiac surgery and interventional cardiology
- Key Team
- Interventional cardiologist, cardiac surgeon, imaging specialist and anaesthesiologist
- Main Approaches
- Transcatheter valve replacement and surgical replacement
- Indian TAVR Series
- 8% one-year all-cause mortality in cited 25-patient series
- TAVR Functional Outcome
- 80% in good functional class at discharge in cited series
- TAVR Pacemaker Rate
- 16% in the cited early Indian series
- Second Indian TAVR Series
- 2.3% procedural mortality among 84 intermediate- and high-risk patients
- Low-Risk Five-Year Comparison
- 15.5% death/disabling stroke with TAVR versus 16.4% with surgery in cited trial
- Imaging
- Detailed CT planning for transcatheter valve sizing and access
- Valve Sizing
- Should be performed according to individual anatomy
- Heart Team
- Interventional cardiologist and cardiac surgeon should jointly assess the case
- Surgical Option
- Conventional or minimally invasive valve replacement for selected patients
- Anaesthesia
- Approach differs between transcatheter and surgical procedures
- Valve Systems
- Ask which specific devices are available
- Durability
- Long-term valve durability should be discussed, particularly in younger patients
- Accreditation
- Verify JCI and NABH accreditation
- Outcome Data
- Request procedure-specific mortality and complication rates
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
In Brief
For Iraqi patients considering heart valve replacement in India, the key decision is not simply TAVR versus surgery. The page 4 visual checklist highlights four factors that should guide hospital selection: availability of both techniques, multidisciplinary heart-team decision-making, technique-specific outcome data and open discussion of long-term valve durability. Detailed CT-based planning is particularly important when transcatheter replacement is being considered.
Why the Choice of Valve Specialist in India Matters as Much as the Choice of Technique
Based on my interactions with international patients, the published data comparing these two approaches is genuinely nuanced, and India has its own growing body of real experience with the newer transcatheter technique specifically. An early Indian single-centre series of twenty-five transcatheter aortic valve replacement patients reported a one-year all-cause mortality of 8 percent, with 80 percent of patients in a good functional class at discharge, though 16 percent required a permanent pacemaker afterward, a recognised complication of this specific technique. A separate Indian series across two armed forces cardiac centres, covering 84 intermediate and high-risk patients, reported a procedural mortality of just 2.3 percent. Internationally, a major randomised trial in low-risk patients published in 2025 found five-year outcomes were closely comparable between the two approaches, with a combined rate of death or disabling stroke of 15.5 percent for transcatheter replacement and 16.4 percent for surgical replacement, a difference that was not statistically significant. Longer-term data from a separate ten-year study, however, found surgical replacement associated with meaningfully better ten-year survival in a population with somewhat different baseline characteristics, a reminder that valve durability and very long-term outcomes are still being actively studied for the newer technique. This is precisely why the specific factors in your case, valve anatomy, age, and overall surgical risk, should determine which approach is recommended, not a hospital’s general preference for one technique.
How Patients from Iraq Can Verify a Heart Valve Hospital’s Accreditation in India
The fastest filter I recommend to every Iraqi patient calling about valve replacement is verifiable accreditation, not marketing language. Joint Commission International, JCI, audits a hospital’s overall clinical safety systems against the same standard used across the United States and Europe. The National Accreditation Board for Hospitals and Healthcare Providers, NABH, is India’s own domestic equivalent, and in my experience of 24 years advising patients on this exact decision, a centre holding both marks together is a meaningfully stronger signal than either alone. For heart valve replacement specifically, ask one further, very direct question: does this hospital offer both transcatheter and surgical valve replacement under one roof, with a genuine multidisciplinary heart team deciding between them, or does it perform only one technique and therefore has an inherent bias toward recommending it regardless of your specific case.
Heart Valve Volume and Technique-Selection Criteria That Predict Outcomes in India
Based on my interactions with dozens of cardiac valve programmes over the years, a centre’s ability to offer both techniques and choose objectively between them, rather than its volume in one procedure alone, is one of the clearest predictors of a good outcome. Ask directly, in writing:
- Does a multidisciplinary heart team, including both an interventional cardiologist and a cardiac surgeon, jointly evaluate my case before recommending transcatheter or surgical replacement?
- What is this centre's own procedural mortality and permanent pacemaker rate specifically for transcatheter replacement, not simply a general valve replacement statistic?
- Given my specific age and risk profile, what does the current evidence suggest about long-term valve durability for each approach in a patient like me?
- If I am a candidate for either approach, what specific factors in my case tipped the recommendation toward one technique over the other?
A centre confident in its own reasoning will answer these specifically. A centre that recommends its single available technique regardless of your specific case deserves a second opinion before you commit.
Vetting a Heart Valve Hospital in India: A Guide for Patients from Iraq
Questions Patients from Iraq Should Ask About the Heart Valve Team in India
Heart valve replacement, particularly the transcatheter approach, is never genuinely the work of one specialist alone. In my experience of 24 years watching these programmes operate, the strongest units bring together an interventional cardiologist experienced specifically in transcatheter valve technique, a cardiac surgeon available for surgical backup or as the primary operator for surgical cases, and an imaging specialist to precisely assess valve anatomy and size before the procedure, since inaccurate sizing is a recognised cause of complications in transcatheter replacement specifically. An anaesthesiologist experienced in managing both conscious sedation for transfemoral transcatheter cases and full general anaesthesia for surgical cases rounds out the team, since the anaesthetic approach differs meaningfully between the two techniques. Ask specifically who fills each of these roles for your case, and confirm that a genuine multidisciplinary heart team meeting, not a single cardiologist’s opinion, determined your recommended approach.
Heart Valve Technology Standards in India That Patients from Iraq Should Check
The specific technology and imaging available change how precisely a team can plan either approach. Ask whether detailed CT imaging is used to plan transcatheter valve sizing and access route before the procedure, since this level of planning meaningfully reduces the risk of complications such as paravalvular leak, the small gap that can form around an incorrectly sized valve. Ask which specific valve systems the hospital has access to, since different manufacturers’ devices have different size ranges and may suit different anatomies better. For surgical candidates, ask whether minimally invasive surgical valve replacement, a smaller-incision alternative to full open-heart surgery, is genuinely available for appropriately selected patients, since this can meaningfully shorten recovery time compared with a traditional full sternotomy. Ask directly which of these specific capabilities apply to your case, not simply whether the hospital owns the equipment somewhere in the building.
Red Flags Patients from Iraq Should Watch For When Choosing a Heart Valve Hospital in India
Over the years, certain patterns have become reliable warning signs for me. A hospital that offers only transcatheter or only surgical valve replacement, and therefore recommends that single technique for nearly every patient, has an inherent conflict of interest in its own recommendation. A centre that cannot state its own procedure-specific mortality and complication rates, offering only a general reassurance about valve replacement safety, has not given you information you can use. A centre that does not mention long-term valve durability considerations when discussing a younger patient’s treatment options has not given you the complete picture needed for a decision that will affect decades of your life. And a centre that skips detailed pre-procedure CT imaging for a transcatheter case, relying only on standard echocardiography, is planning your valve sizing with less information than current best practice supports.
Factors Every Patient from Iraq Should Weigh Before Choosing Heart Valve Replacement in India

A Closing Thought for Iraqi Families
Heart valve replacement now offers two genuinely effective approaches, and the right choice depends on your specific anatomy, age, and risk profile, not a hospital’s single available technique or a general preference for whichever sounds less invasive. Based on my interactions with international patients over more than two decades, the patients who ask about multidisciplinary decision-making, technique-specific outcome data, and long-term durability considerations consistently make better-informed decisions than those who accept a single recommendation without question. My role, and the role of any advisor a patient works with, should be to help you ask these exact questions and confirm honestly that the specific team and specific hospital in front of you are the right fit for your exact case. Iraq’s patients deserve the same standard of scrutiny in this decision as any patient anywhere else in the world.
Sources & Further Reading
- Joint Commission International (JCI) — Accredited Organizations Directory (jointcommissioninternational.org)
- National Accreditation Board for Hospitals & Healthcare Providers (NABH), India (nabh.co)
- ScienceDirect — Transcatheter Aortic Valve Replacement in India: Early Experience and Outcomes (sciencedirect.com)
- PubMed Central — Transcatheter Aortic Valve Replacement in the Developing World: Indian Experience (pmc.ncbi.nlm.nih.gov)
- Journal of the American College of Cardiology (JACC) — 5-Year Outcomes After TAVR or SAVR in Low-Risk Patients (jacc.org)
Frequently Asked Questions by Iraqi Patients about Selecting a Heart Valve Surgeon and Hospital in India
Can Iraqi patients receive heart valve replacement in India?
Yes. The source specifically addresses Iraqi patients considering heart valve replacement in India and discusses both surgical and transcatheter approaches.
Can Iraqi patients receive TAVR in India?
Yes. TAVR is discussed as a treatment option for selected patients, with the final decision depending on valve anatomy, age, surgical risk and multidisciplinary heart-team assessment.
Is TAVR better than surgical valve replacement for Iraqi patients?
Not universally. The source states that neither approach is automatically superior. The appropriate technique depends on the patient's anatomy, age, surgical risk and long-term treatment considerations.
What is the reported TAVR outcome in the Indian study cited in the guide?
The cited 25-patient Indian series reported 8% one-year all-cause mortality, 80% of patients in good functional class at discharge and a 16% permanent pacemaker rate.
What should Iraqi patients ask about TAVR pacemaker risk?
They should request the hospital's own permanent pacemaker rate specifically for TAVR rather than relying on a general valve-surgery complication rate.
Is CT imaging required before TAVR for Iraqi patients?
The guide recommends detailed CT imaging for transcatheter valve sizing and access-route planning. This helps the heart team assess anatomy and reduce complications such as paravalvular leak.
Can Iraqi patients receive minimally invasive surgical valve replacement in India?
The source recommends asking whether minimally invasive surgical valve replacement is available for appropriately selected patients. It may offer a smaller incision than conventional full sternotomy.
Which specialists should assess an Iraqi patient for valve replacement in India?
The guide recommends a multidisciplinary team involving an interventional cardiologist, cardiac surgeon, imaging specialist and anaesthesiologist. The final recommendation should come from the heart team rather than one specialist alone.
Should Iraqi patients ask about long-term valve durability?
Yes. Durability is particularly important when evaluating younger patients because the treatment decision can affect many years of future care. The source recommends comparing long-term considerations for both transcatheter and surgical approaches.
What should Iraqi patients check before choosing a heart valve hospital in India?
They should verify JCI and NABH accreditation, confirm that both treatment approaches are genuinely available, request technique-specific outcome data, ensure multidisciplinary assessment and confirm that detailed imaging is used for transcatheter planning.
Page Summary
Heart valve replacement can be performed through surgical or transcatheter approaches, and the source stresses that neither should automatically be considered superior. Published Indian TAVR experience and international comparative data demonstrate why outcomes must be interpreted according to patient risk, anatomy, age and follow-up period rather than through a single headline statistic.
For Iraqi patients travelling to India, an appropriate hospital should ideally have access to both transcatheter and surgical replacement, a multidisciplinary heart team, procedure-specific outcome data and detailed imaging capability. Long-term valve durability should also be discussed, particularly when treatment is being considered for younger patients.
Citation Block
| Field | Details |
|---|---|
| Article / Topic | Selecting the Best Heart Valve Replacement Surgeons and Hospitals in India |
| Primary Patients | Patients from Iraq |
| Treatment Area | Heart valve replacement |
| Main Approaches | Transcatheter and surgical valve replacement |
| Early Indian TAVR Series | 25 patients |
| Indian TAVR One-Year Mortality | 8% in cited series |
| Indian TAVR Functional Outcome | 80% in good functional class at discharge |
| Permanent Pacemaker Rate | 16% in cited early TAVR series |
| Second Indian TAVR Series | 84 intermediate- and high-risk patients |
| Second Series Procedural Mortality | 2.3% |
| Low-Risk Five-Year Trial | 15.5% TAVR versus 16.4% surgical death/disabling stroke |
| Accreditation | JCI and NABH |
| Hospital Capability | Ideally both transcatheter and surgical replacement |
| Heart Team | Interventional cardiologist and cardiac surgeon |
| Imaging Specialist | Assesses valve anatomy and sizing |
| Anaesthesiologist | Experience with transcatheter sedation and surgical anaesthesia |
| TAVR Planning | Detailed CT imaging for sizing and access |
| Valve Sizing | Important for reducing complications such as paravalvular leak |
| Valve Systems | Different devices may suit different anatomies |
| Minimally Invasive Surgery | Ask whether available for appropriate surgical candidates |
| Durability | Long-term considerations should be discussed |
| Outcome Data | Request procedure-specific mortality and complication rates |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Iraq














Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
Indian Health Guru Consultants proudly assists patients from Iraq and surrounding Middle Eastern countries in accessing advanced, affordable and trusted medical treatment in India. Our team provides complete support for medical opinions, hospital selection, treatment planning, visa assistance, travel coordination, accommodation and post-treatment follow-up.
We regularly serve patients from:
- Iraq
- Turkey
- Iran
- Kuwait
- Jordan
- Syria
- Qatar
- Bahrain
- Oman
- Yemen
- Saudi Arabia
- United Arab Emirates
No matter where you are located, our experienced team is committed to making your medical journey to India safe, smooth, transparent and stress-free from the first enquiry to your return home.
From Iraq to India: Your Complete Patient Guide
- Paediatric Orthopaedic Surgery in India for Iraqis
- Cancer Treatment in India for Iraqi Patients
- Cosmetic and Aesthetic Surgery in India for Iraqis
- Radiotherapy and Modern Cancer Treatment in India for Iraqis
- Dental Surgery in India for Iraqis
- Breast Cancer Treatment in India for Iraqi Patients
- Brain Tumour Surgery in India for Iraqi Patients
- Knee Surgery in India for Iraqis
- Oral and Maxillofacial Surgery in India for Iraqis
- Spine Surgery in India for Iraqis
- IVF and Fertility Treatment in India for Iraqis
- Plastic and Reconstructive Surgery in India for Iraqis
- Parkinson's Treatment and DBS Surgery in India for Iraqis
- Laparoscopic and Robotic Myomectomy in India for Iraqis
- Gamma Knife Treatment in India for Iraqis
- Complex Joint Revision Surgery in India for Iraqis
- Scoliosis Correction Surgery in India for Iraqis
- Leukemia, Lymphoma and Blood Cancer Treatment in India for Iraqis